Hip impingement syndrome
This occurs when the hip muscles do not coordinate well to support the hip in its joint, leading to irritation within the hip joint.



Other names for hip impingement syndrome
- Femoroacetabular Impingement
- FAI (Femoroacetabular Impingement)
- Hip impingement syndrome
What is hip impingement syndrome?
Hip impingement syndrome involves a combination of symptoms, physical examination findings, and bone abnormalities visible on imaging. Also known as femoroacetabular impingement syndrome, it cannot be diagnosed based on bone abnormalities alone.1
The hip joint functions like a ball-and-socket joint. The head of the femur, the "ball," fits into the acetabulum, the "socket" in the pelvis. Normally, these surfaces glide smoothly against one another. When there is catching, the bones come into abnormal contact during certain movements.
There are three types of hip impingement syndrome:
- Cam type: The junction between the head and neck of the femur is less rounded. It may come into contact with the rim of the acetabulum sooner during certain movements.2
- Pincer type: The acetabulum covers a larger portion of the femoral head. During certain movements, the femoral neck can compress the labrum against the rim of the acetabulum.2
- Mixed type: The hip has both a cam shape and a pincer shape.
10 Quick Tips to Understand Your Pain
One tip a day for 10 days to help you better understand your pain. About a 2-minute read.
The syndrome may be accompanied by damage to the labrum—the ring of cartilage that lines the acetabulum—or to the articular cartilage. However, bone abnormalities and changes in the labrum are also observed in people without pain. Imaging findings must therefore be interpreted in conjunction with symptoms and physical examination.3
What causes hip impingement syndrome?
There is no single cause of hip impingement syndrome. The shape of the bones and hip movements can contribute to the symptoms. A cam or pincer shape does not automatically cause pain.1, 3
The evaluation examines bone structure, hip function, and the activities that trigger symptoms.
Bone structures examined:- Abnormalities in the shape of the femoral head (cam) or acetabulum (pincer)
- The cam-shaped deformity can develop during growth. It is more commonly seen in certain adolescents who participate in high-level sports, but the available data do not allow us to predict who will develop symptoms.
- Strength of the muscles that flex and extend the hip
- Hip Mobility During Movement
- Duration, Intensity, and Progression of Sports Activities
- Strength of the glutes and the muscles that rotate the hip
Reduced strength, mobility, or coordination may be observed during the evaluation. These findings help guide treatment decisions, but they do not prove the cause of the syndrome.
Situations that may worsen symptoms:- Sudden increase in training volume
- Resuming sports activity after a period of inactivity
- Sports that require you to frequently bring your knee toward your chest
- A workout that clearly replicates the symptoms
What are the risk factors for developing hip impingement syndrome?
The risk factors for painful catch syndrome remain difficult to pinpoint. Certain associations are better documented regarding the development of the CAM form in adolescent athletes. This association does not mean that a sport causes the syndrome or that a person with this form will experience pain. Symptoms can appear at various ages.2, 3
Activities that may cause symptoms in some people:- Hockey and skating
- Dance and gymnastics
- Running
- Martial arts
- Soccer and basketball
- Volleyball
- The presence of a cam or pinched form on imaging, when it also corresponds to the symptoms and physical examination
- A rapid increase in an activity that often requires bringing the knee toward the torso or rotating the thigh
- Mobility, strength, or coordination that do not meet the demands of the activity
- A history of hip pain that recurs during certain activities
Did you know? A cam-shaped lesion can be visible without causing pain. A review of 26 studies found it in about 37% of asymptomatic hips, with estimates of about 23% in the general population and 55% among athletes. These figures vary depending on the population and the definitions used.3
What are the symptoms of hip impingement syndrome?
Hip impingement syndrome can cause pain in the groin or hip, especially during certain movements or after sitting for a long time. Some people also experience stiffness, a clicking sensation, or a locking sensation.
Pain location:- Primarily in the groin crease (in front of the hip)
- May radiate to the buttock, outer thigh, or even the knee
- Sometimes described as a "C" shape around the hip
- The pain may increase when you pull your knee toward your chest.
- Worse with prolonged sitting
- Pain may increase during activities in which the leg bears the body's weight.
- A sensation of clicking, snapping, or cracking in the hip
- Hip stiffness
- Difficulty moving the hip as far as before
- Occasional feeling of hip catching or locking
- Running or walking with long strides
- Climbing stairs or hiking in the mountains
- Deep squats
- Getting up from a chair or out of a car
- Prolonged sitting (at a desk, in a car, on a plane)
How is hip impingement syndrome diagnosed?
The diagnosis of hip impingement syndrome requires consistent symptoms, physical examination findings, and imaging findings. None of these factors alone confirms the diagnosis.1
Clinical Assessment:Your physiotherapist or doctor will ask questions about:
- The exact location of your pain
- Movements and activities that worsen the pain
- How long you have had symptoms
- Your sports or work activities
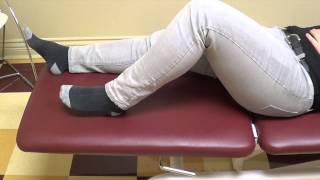
The FADIR test combines three movements: hip flexion, bringing the thigh toward the other leg, and rotating the thigh inward. The recurrence of pain may indicate a problem within the joint, but this test lacks the precision needed to identify snapping hip syndrome. Therefore, it does not confirm the diagnosis on its own.4
Imaging required to confirm the diagnosis:- X-rays: They show the shape of the bones. The alpha angle helps describe the cam shape, while the center-edge angle helps describe the coverage of the femoral head by the acetabulum.
- Magnetic Resonance Imaging (MRI): This test produces detailed images of the labrum and cartilage when clinically indicated.
Cam or pincer deformities may be visible in people who are pain-free. The healthcare professional therefore interprets the imaging findings in conjunction with the symptoms and physical examination.3, 1
When should you see a physiotherapist for hip impingement syndrome?
See a physical therapist if you have persistent groin or hip pain that limits your activities or is accompanied by repeated episodes of stiffness.
An evaluation helps assess mobility, strength, the movements that trigger symptoms, and the signs that warrant medical consultation or imaging.
- Pain that persists or recurs during your daily activities, sports, or leisure activities
A recurring worsening of symptoms following a change in training may indicate that the duration, intensity, or type of activity needs to be adjusted. An evaluation is recommended if symptoms persist despite this adjustment.
You do not need a doctor's referral to see a physical therapist. If your condition requires a medical evaluation or imaging, your physical therapist can refer you to the appropriate provider.
What are the physiotherapy treatments for hip impingement syndrome?
Physical therapy treats hip impingement syndrome through education, activity modifications, and progressive exercises. Non-surgical treatment is a recognized initial option. The program may include strengthening the glutes and core, range-of-motion exercises, and joint mobilization when indicated by the evaluation.1, 5
Initial assessment:Your physical therapist will assess:
- Your joint mobility
- The strength of the glutes and the muscles that stabilize the hip or rotate the thigh
- The quality of your movements
- Your walking pattern
- Your physical activity and sports habits
- Gluteal muscles (gluteus medius and gluteus maximus)
- Muscles that rotate the thigh outward
- Pelvic and Core Stabilizing Muscles
- Techniques to Help You Move Your Hip Further
- Mobilizations in directions that do not worsen impingement
- Identifying problematic positions and movements
- Strategies to modify activities without stopping them completely
- A Gradual Return to Activities
- Developing movement strategies tailored to the targeted activities
The program aims to improve the activities that matter to you. A review of five small trials found better short-term outcomes with supervised, active programs than with passive or unsupervised approaches. The average follow-up period was about nine weeks, which leaves some uncertainty about the long-term effects.6
What to do at home for hip impingement syndrome?
At home, you can temporarily adjust the movements that significantly worsen your symptoms and continue with the activities that your hip can handle. Strengthening exercises can be part of the plan when they are appropriate based on your evaluation.
Possible activities based on your tolerance:- Swimming
- Stationary bike with a properly adjusted seat
- Moderate walking on flat ground
You can squat less deeply, take a break from prolonged sitting, or avoid forced stretching if these actions clearly worsen your symptoms. These adjustments are meant to help you maintain a level of activity you can tolerate and then gradually increase your range of motion based on how your body responds.
An activity that is tolerated can generally be continued, whereas an activity that causes a marked or lasting increase in symptoms may need to be temporarily modified. There is no universal list of permitted or prohibited activities.5
Reduced mobility may be a factor, but it is not automatically the cause of the pain. The evaluation is designed to determine whether mobility exercises are helpful and how far you can move comfortably.
Practical daily tips:- Take regular breaks if you sit for long periods at work
- To get out of the car, you can swing both legs out at the same time if that feels more comfortable.
- If you sleep on your side, place a pillow between your thighs
- Shift your weight differently or change your position if putting weight on one hip makes your symptoms worse.
Exercises can target the glutes, the muscles that rotate the thigh, or the core muscles. The choice of movement, number of repetitions, and resistance depends on your tolerance, abilities, and goals.
Core exercises may be included in the program, but they are not required for everyone. The plan includes exercises that address the needs identified during the assessment.6
If your symptoms do not improve or begin to further limit your activities, an evaluation can confirm the diagnosis and adjust the treatment plan.
Pain intensity does not directly reflect the condition of the tissues. Persistent symptoms warrant a reassessment of the duration and intensity of activities, movements, and other factors that may influence pain.
What is the recovery time for hip impingement syndrome?
There is no set recovery time for hip impingement syndrome. A review of this syndrome and other types of hip pain not related to osteoarthritis reports a satisfactory response to nonsurgical treatment in approximately 54% of participants. The 95% confidence interval, which describes the uncertainty surrounding this estimate, ranged from 32% to 76%. These figures do not predict an individual’s response.7
Progress is determined based on changes in symptoms, functional status, and the demands of the targeted activity. The program is reassessed when the response does not meet the objectives.
- Pain and function may progress at different rates. Follow-up care takes both into account.
- Symptoms, Function, and Goals at the Start of Follow-Up
- How the Hip Responds to Activities and Exercises
- Option to tailor the program to the activities that matter to you
- Other health problems or factors that affect pain and activity
Non-surgical treatments are a recognized initial option. If symptoms persist despite an appropriate treatment plan, a medical consultation can weigh the benefits of continuing rehabilitation against surgical options, based on the individual’s diagnosis, goals, and preferences.1
Non-surgical treatments encompass several approaches. Small, short-term trials show that supervised, active programs are more effective than passive or unsupervised approaches, but they do not allow us to define an ideal program for each individual.6, 7
Hip surgery remains an option for some people. If you do not see any improvement despite following a physical therapy program as directed, a reevaluation and possibly imaging may be recommended to explore other options. The intensity and duration of the program are important, and you should discuss the timing of the reevaluation with your physical therapist based on your progress.
Need professional advice?
Our physical therapists can assess your condition and provide you with a personalized treatment plan.
Make an appointmentWhat sources does this article draw on?
This article is based on the following seven scientific sources. Each number listed in the text corresponds to the relevant reference.
Links open in a new tab.
- Griffin DR, Dickenson EJ, O'Donnell J, Agricola R, Awan T, Beck M, et al. The Warwick Agreement on femoroacetabular impingement syndrome (FAI syndrome): an international consensus statement. Br J Sports Med. 2016;50(19):1169-76. (Back to sections: 1, 2, 3, 4, 5, 6)
- Ejnisman L, Ricioli Júnior W, Queiroz MC, Vicente JRN, Croci AT, Polesello GC. Femoroacetabular Impingement and Acetabular Labral Tears - Part 1: Pathophysiology and Biomechanics. Rev Bras Ortop (Sao Paulo). 2020;55(5):518-522. (Back to sections: 1, 2, 3)
- Frank JM, Harris JD, Erickson BJ, Slikker W, Bush-Joseph CA, Salata MJ, et al. Prevalence of Imaging Findings Suggestive of Femoroacetabular Impingement in Asymptomatic Volunteers: A Systematic Review. Arthroscopy. 2015;31(6):1199-204. (Back to sections: 1, 2, 3, 4, 5)
- Reiman MP, Goode AP, Cook CE, Hölmich P, Thorborg K. Diagnostic accuracy of clinical tests for the diagnosis of femoroacetabular impingement and labral tears of the hip: a systematic review with meta-analysis. Br J Sports Med. 2015;49(12):811. (Back to section: 1)
- Mallets E, Turner A, Durbin J, Bader A, Murray L. SHORT-TERM OUTCOMES OF CONSERVATIVE TREATMENT FOR FEMOROACETABULAR IMPINGEMENT: A SYSTEMATIC REVIEW AND META-ANALYSIS. Int J Sports Phys Ther. 2019;14(4):514-524. (Back to sections: 1, 2)
- Hoit G, Whelan DB, Dwyer T, Ajrawat P, Chahal J. Physiotherapy as an Initial Treatment Option for Femoroacetabular Impingement: A Systematic Review of the Literature and Meta-analysis of 5 Randomized Controlled Trials. Am J Sports Med. 2020;48(8):2042-2050. (Back to sections: 1, 2, 3)
- Probst DT, Sookochoff MF, Harris-Hayes M, Prather H, Lipsey KL, Cheng AL. What Is the Response Rate to Nonoperative Treatment for Hip-Related Pain? A Systematic Review with Meta-analysis. J Orthop Sports Phys Ther. 2023;53(5):286–306. (Back to sections: 1, 2)
Videos in this category


Other conditions

Hip osteoarthritis is the normal wear and tear of the hip joint. It is often said that osteoarthritis is the wear and tear of the cartilage between our bones. That is true, but it involves more than just the cartilage. Cartilage is a tissue that acts as a cushion between the surfaces of our bones and allows our joints to glide smoothly and move fluidly.
This is normal wear and tear of the knee joint. It’s often said that osteoarthritis is the wearing down of the cartilage between our bones. That’s true, but it’s more than just the cartilage. Cartilage is a tissue that acts as a cushion between the surfaces of our bones and allows our joints to glide smoothly and move fluidly.
It is an inflammation of the subacromial bursa in the shoulder joint.
A bursa is a small, thin sac filled with fluid that is found in many of the body's joints. This small sac acts as a cushion within the joint and lubricates the structures that are subject to increased friction.
It is a tissue that surrounds the shoulder and helps keep the shoulder bone in place within the joint. The capsule helps keep the joint stable.
Neck pain is a general term used to describe pain in the neck that has no specific cause, such as an accident or a sudden awkward movement. Neck pain is therefore synonymous with “my neck hurts, and nothing in particular happened.”
In both types of injury, pain is felt in the neck and then radiates into the arm, or vice versa.
Make an appointment now
We offer a three-pronged quality assurance approach: optimized treatment time, a second opinion from a physical therapist, and ongoing expertise to ensure effective care tailored to your needs.

Customer satisfaction is our top priority
At Physioactif, excellence guides everything we do, but our patients are the best ones to tell you about it. Take a look at their verified reviews to get a real sense of their experience.









Discover our physical therapy clinics
We have locations in several areas to better serve you.
Blainville
190 Bas-de-Sainte-Thérèse Road, Suite 110,
Blainville, Quebec
J7B 1A7
Located in Blainville, near Rosemère, the Physioactif clinic is easily accessible to residents of the area and the surrounding communities
Boucherville
690 Rue de Montbrun, Suite S,
Boucherville, Quebec
J4B 8H2
Located in Boucherville, the Physioactif clinic is easily accessible to people in the area
Laval
3224 Jean-Béraud Ave., Suite 220, Laval,
QC H7T 2S4
Located in Chomedey, in the heart of Laval, the Physioactif clinic is easily accessible to people in the area
Montreal
8801 Lajeunesse Street,
Montreal,
QC H2M 1R8
Located in Ahuntsic, near Villeray, the Physioactif clinic is easily accessible to residents of both neighborhoods
Saint-Eustache
180 25th Avenue, Suite
201 Saint-Eustache
QC J7P 2V2
Located in Saint-Eustache, the Physioactif clinic is easily accessible to residents of the area and the surrounding communities
Vaudreuil
21 Cité-des-Jeunes Boulevard, Suite 240,
Vaudreuil-Dorion, Quebec
J7V 0N3
Located in Vaudreuil-Dorion, the Physioactif clinic is easily accessible to people in the area
Make an appointment now
